A reader asks:
As a fan of your blog, I had a quick question that I was hoping I could get your advice on. I’m a 20 year old male, living in Australia where it’s currently a Wednesday night. On Saturday night I will be attending the final session of a fitness and self protection course I signed up to at college. According to friends of mine who had done the course before, the final session is akin to basic training for army recruits! (Here’s where you come in)
I’ve been told by friends that practically from Saturday night to Sunday lunch time they deprive you of sleep and run you through non stop intense fitness exercises like running, push-ups, sit-ups etc.
What I was thinking of doing was perhaps changing my sleeping pattern so my body will effectively not be missing out on sleep. Let’s say I stayed up tomorrow night (Thursday night), slept all of Friday, stayed up all Friday night, and slept all Saturday - come Saturday night my body will expect to be awake and it won’t be as gruelling – right? Would this be effective? Is this enough time for my body to adjust or would I just be making things worse?
It's too short of a time for you to adjust your biological clock- the body is only capable of adjusting 1 hr each day. You are essentially facing 2 problems- 1) sleep deprivation and 2) circadian rhythm dysfunction (you will be expected to be active during a time when your body expects you to be asleep).
I recommend that you keep your normal sleep schedule and then try to take a 2-3 hour nap right before your final course begins. If allowed during your course, caffeine and Provigil would be helpful. Bright light exposure during your course, if possible, would also be helpful.
Hope this helps
Michael Rack, MD
Wednesday, June 06, 2007


Tuesday, June 05, 2007
Saturday, June 02, 2007
Treatment of Alcohol-related sleep disorders
The following is from an article I wrote for Medlink Neurology on "Sleep disorders associated with alcohol use and abuse." It is copyrighted by Medlink Neurology:
For the sleep disorders occurring during alcohol intake, cessation of alcohol use is often the only necessary treatment. Treatment of the sleep apnea exacerbated by alcohol requires avoidance of alcohol intake at least for 4 hours to 6 hours before going to bed. If the apnea does not resolve with alcohol cessation, then standard treatments for obstructive sleep apnea, such as nasal continuous positive airway pressure, are required. The hypersomnia that can occur with alcohol use is usually eliminated after 1 day or 2 days without alcohol, but insomnia may actually worsen for the first 2 weeks to 7 weeks off alcohol. It is important not to restart the alcohol even at a low dose to ameliorate this problem; similarly, use of hypnotics is contraindicated because of the cross-tolerance with alcohol and the potential for both abuse and dependence. Sedating antihistamines or low doses of sedating antidepressants can be used for temporary relief when insomnia episodes are particularly severe. Patients should be reassured that in most cases the insomnia gradually gets better.
Behavioral treatments for insomnia with good sleep hygiene, relaxation training, desensitization, or sleep restriction should be used during the withdrawal period. If evidence develops for depression then a sedating antidepressant (eg, amitriptyline or mirtazapine) may be helpful for both sleep and depression.
As mentioned above, sleep abnormalities in alcoholics can persist for several years after alcohol cessation; this sleep disturbance may contribute to relapse of alcoholism. Various medications and psychotherapy techniques have been used to treat this sleep disturbance. Gabapentin, at doses of 300 mg to 1800 mg at bedtime, is useful in treating insomnia in abstinent alcohol-dependent outpatients and appears to be more effective than trazodone (Karam-Hage and Brower 2003). Although quetiapine is of potential benefit for this condition (Monnelly et al 2004; Sattar et al 2004), the risk of tardive dyskinesia and metabolic abnormalities associated with the use of atypical antipsychotics suggests that they should be used cautiously, if at all, for insomnia. Cognitive-behavioral treatments, including stimulus control, sleep restriction, and cognitive restructuring, have been shown to improve subjective sleep quality in recovering alcoholics (Currie et al 2004).
The melatonin receptor agonist Ramelteon (Rozerem-Takeda) is an option for treating insomnia in recovering alcoholics, though controlled trials are lacking. Ramelteon is not a controlled substance, and has essentially no abuse liability (Anonymous 2005; Griffiths and Johnson 2005). It is approved for the treatment of insomnia characterized by difficulty with sleep onset (Laustsen and Andersen 2006). The standard dose is 8 mg, taken within 30 minutes of going to bed. It is metabolized by cytochrome p450 enzyme 1A2 but does not appear to inhibit or induce this enzyme (Laustsen and Andersen 2006). It should not be used in combination with fluvoxamine, a strong 1A2 inhibitor (Takeda Pharmaceuticals 2005).
Acamprosate (Campral- Forest Pharmaceuticals) is a glutamate modulator that is FDA-approved for the maintenance of abstinence from alcohol in patients with alcohol dependence who are abstinent at treatment initiation (Forest Pharmaceuticals 2005). A recent parallel double-blind placebo-controlled study found that acamprosate improved sleep quality during early abstinence (Staner et al 2006).
disclaimer: this is not the final edited version that will appear in Medlink Neurology. I encourage you to check out the website for Medlink Neurology for the full version of this article as well as numerous other articles about sleep (a few written by me).
Saturday, May 19, 2007
I don't know much about beds

Occasionally a patient will complain about their mattress or ask me what type of matress I recommend.
I don't have a clue. Mattresses were not covered in medical school, residency, or fellowship.
A good, comfortable mattress is probably important for sleep-but my patients are better off asking a matress salesman than me. If you live in Mississippi, you might want to try Miskellys
I don't have a clue. Mattresses were not covered in medical school, residency, or fellowship.
A good, comfortable mattress is probably important for sleep-but my patients are better off asking a matress salesman than me. If you live in Mississippi, you might want to try Miskellys
Tuesday, April 17, 2007
idiopathic hypersomnia
A reader (Claire) asks: "However he has been unable to diagnose or treat my particular sleep problem and I can find no info anywhere that describes my particular symptoms.I find so much research has been done in some areas but not enough in others in regards to sleep.My problem; I sleep if allowed 10hours a day but am constantly tired. 2 afternoon naps not unusual, but I don’t fall asleep randomly..."
-------------------------------------------------
If a sleep study (polysomnogram) is negative, you may have idiopathic hypersomnia. Consider asking your primary care doctor for a referral to a sleep specialist.
-------------------------------------------------
If a sleep study (polysomnogram) is negative, you may have idiopathic hypersomnia. Consider asking your primary care doctor for a referral to a sleep specialist.
REM-related obstructive sleep apnea
A reader (Franto) asks "Sorry to butt in with this question for you! I had a recent sleep study that showed I am getting v little REM sleep because I start getting hypopneic as soon as I enter into REM and have an arousal. Overall there was little obstruction and no apnea (lowest O2 sat was 91%). The problem was entirely REM specific, and I had good deep sleep. My total REM percentage was only 6.5%. There apparently were several aborted REM episodes. The reason I had the study done was that I have been having unrefreshing sleep and working memory issues for a few years now! My sleep physician wants me to do CPAP study to see if it helps improve my REM. My Q to you is if you see cases like mine at all, since I havent read about such a selective REM condition on the web or Pubmed. I know about UARS but that too involves both REM and NREM. Would CPAP help in such a situation?"
_____________________
Some people have OSA primarily during REM sleep. I found the following in Sleep Medicine Pearls, by Richard B. Berry, MD (2nd edition, page 118):
In patients with excessive daytime sleepiness and significant, REM-specific sleep apnea, treatment is indicated. Other possible causes of daytime sleepiness should be excluded.
The reason for the higher AHI during REM sleep are commplex. REM sleep is not homogenous, and episodes of decreased upper airway muscle activity or ventilatory drive may be the cause of hypopneas or apneas during REM sleep.
In my experience, in many people, OSA is worse during REM sleep. It is unusual for sleep apnea to occur exclusively during REM, but it is possible. I think your sleep physician's advice is reasonable and CPAP is worth a try.
Friday, March 30, 2007
Drowsy Driving


According to the National Sleep Foundation, drowsy driving causes over 100,000 motor vehicle accidents, 71,000 injuries, and 1550 deaths each year. Common causes of drowsy driving include chronic sleep deprivation and untreated sleep disorders, such as obstructive sleep apnea.
A commercial driver’s extended hours of operation can create a scenario of continuous sleep deprivation. Difficulties in adjusting to varying shifts and rotating work schedules can compound the problem. The average adult needs 7 to 9 hours of sleep each day, and it is important to allow for sufficient sleep time. For those who have trouble adjusting to unusual work hours or rotating shifts, medication and/or bright light therapy are sometimes helpful.
Obstructive sleep apnea is present in 2-4% of the middle-aged population. It is more common in commercial drivers due to the high rate of obesity in this population. Obstructive sleep apnea is a disorder in which apneas (breathing pauses) occur during sleep. It is normal for the tissues of the upper airway to be somewhat collapsible during sleep, but in obstructive sleep apnea this tendency is exaggerated. Common symptoms of obstructive sleep apnea include loud snoring, daytime sleepiness, memory/concentration difficulties, and erectile dysfunction. The most common treatment for obstructive sleep apnea is continuous positive airway pressure (CPAP), in which pressurized air is delivered through a nasal mask to the upper airways. The pressurized air acts as a pneumatic splint for the upper airways. Other treatments for obstructive sleep apnea include dental appliances and ENT surgery.
Driving while sleepy is a serious problem, especially for commercial drivers. Any commercial driver with snoring or daytime sleepiness should be evaluated by a sleep specialist to ensure their, and the public’s, safety while driving.
Thursday, March 29, 2007
Why do we Sleep?

Sleep is not an optional enterprise. All mammals do it. So do birds, reptiles, and even fruit flies. Rats deprived of sleep apparently die faster than those deprived of food. Sleep deprivation is a ruthlessly effective means of torture, as the new movie The Lives of Others shows in a stomach-turning scene. Yet the bedrock question—what purpose does sleep serve for us and the rest of the animal kingdom—remains oddly unsettled.
no one knows exactly what the underlying need is.
This Slate article discusses the theory that sleep plays a role in memory consolidation.
Ambien is going Generic Soon
Patients suffering from insomnia may soon sleep better for less thanks to the pending expiration of patents on a number of widely used prescription drugs. This year alone, 10 brand-name medications with revenue exceeding $8.1 billion are expected to lose patent exclusivity, including the widely prescribed sleep medication Ambien (zolpidem tartrate).
Ambien CR is being pushed due to the impending patent expiration of Ambien. Ambien works great for patients who have trouble falling asleep at the beginning of the night, but Ambien CR is better for patients with middle-of-the-night awakenings.
Ambien CR is being pushed due to the impending patent expiration of Ambien. Ambien works great for patients who have trouble falling asleep at the beginning of the night, but Ambien CR is better for patients with middle-of-the-night awakenings.
Sunday, March 11, 2007
Separate Bedrooms
The New York Times reports that many couples sleep in separate bedrooms, often due to either snoring or restless sleep:
According to the National Sleep Foundation in Washington, 75 percent of adults frequently either wake in the night or snore — and many have taken to separate beds just for those reasons. In a report issued Tuesday, the foundation found that more than half the women surveyed, ages 18 to 64, said they slept well only a few nights a week; 43 percent believed their lack of sleep interfered with the next day’s activities.
Stephanie Coontz, director of public education for the Council of Contemporary Families in Chicago, said many couples she interviewed were “confident enough that they have a nice marriage, but they don’t particularly like sleeping in the same room.”
“I don’t think it says anything about their sex lives,” Ms. Coontz said.
Saturday, March 03, 2007
New Sleep Medicine Board Examinations

It's time to register for the sleep medicine examinations. Pretty much everyone with sleep experience is elgible during the "grandfathering" period. For internists/pulmonologists, you can find out more info here. The early registration period is March 1 to May 1 2007. Here is the site for psychiatrists/neurologists. Here is the site for ENT physicians. This is the site for pediatricians.
------------------------------------------------------------
Family practitioners are out of luck for now; their board is not yet sponsoring the new examination.
---------------
The cost of the exam for those whose primary board is the American Board of Internal Medicine is $1575. The application was very easy- took me about 2 minutes online, and it will take me about another minute to fax my sleep board certification certificate (from the old certifying organization) to the American Board of Internal Medicine.
----------------------------
The American Academy of Sleep Medicine site has frequent updates about the board exams.
Monday, February 26, 2007
sleep apnea and cardiovascuar disease

The evidence linking obstructive sleep apnea to cardiovascular disease continues to grow. Obstructive sleep apnea (OSA) is a thought to be a risk factor for the development of hypertension, stroke, coronary artery disease, and congestive heart failure. The evidence is strongest for hypertension. A recent study adds to the evidence linking OSA to stroke:
But the real question, Dr. Mohsenin said, is whether there is an independent association between sleep apnea and stroke, and a recent study on which he was an author shows that there is indeed such an association.
In the observational cohort study of 697 patients with obstructive sleep apnea and 325 controls (mean apnea-hypopnea index of 35 vs. 2 in the patients and controls, respectively), obstructive sleep apnea was found to have a statistically significant association with stroke or death (hazard ratio of 1.91) after adjustment for numerous factors, including age, sex, race, smoking status, alcohol consumption, body mass index, diabetes, hyperlipidemia, atrial fibrillation, and hypertension.
A trend analysis also showed a significant dose-response relationship between sleep apnea severity at baseline and development of a composite end point of stroke or death from any cause (N. Engl. J. Med. 2005;353:2034–41).
While randomized controlled trials are needed to firmly establish a causal link between sleep apnea and stroke—to “put the last nail in the coffin and say, ‘ok, sleep apnea is indeed a cause of stroke in a high-risk patient population,’” as Dr. Mohsenin put it, the findings increasingly suggest this is the case. Also, sleep apnea occurs as commonly in transient ischemic attack as it does in stroke, further underscoring the need for sleep apnea treatment in affected patients, he noted.
Additionally, a number of studies have shown that sleep apnea is associated with worse functional outcomes in stroke patients, Dr. Mohsenin said.
Patients with stroke who have sleep apnea have been shown to have more delirium, depression, impaired functional capacity, longer rehabilitation time, and longer hospitalization, he said.
“Sleep apnea does affect the outcome of stroke,” he said, noting that in some studies these effects lasted out to 12 months.
Patients who have had a stroke should be evaluated for sleep disordered breathing, he advised.
That the treatment of OSA improves cardiovascular outcomes is an unproven assumption. We know that in sleep apnea patients, CPAP can improve cardiac functioning (ejection fraction) and reduce blood pressure. However, it has not been proven that CPAP improves mortality or decreases the rate of myocardial infarction. A randomized controlled trial looking at this question would be difficult to carry out.
Kleine-Levin Syndrome

Miss Hoyland, a 26-year-old youth charity worker, is one of only a handful of Britons to suffer a rare sleep disorder which can cause her to stay in bed for up to a week at a time.
She wakes only to snack on whatever food is available and visit the bathroom before relapsing into a dream-like state.
The attacks started when she was 17 and studying for her A-levels - forcing her to take weeks off school to sleep.
After graduating she was working as a sales assistant when one day she became woozy and had to sit down, then minutes later she was snoozing in the staff room.
Since then she has suffered 'sleeping episodes' for a week every two months.
Since then she has suffered 'sleeping episodes' for a week every two months.
It took a further eight years until specialists correctly diagnosed her with Kleine-Levin Syndrome, known more commonly as sleeping beauty disease.
Thought to be caused by a chemical abnormality in the base of the brain where sleep and appetite is governed, the incurable neurological disorder affects fewer than 1,000 victims worldwide.
Sufferers are often uncontrollably hungry when they awake and it can affect sex drive as well as behaviour.
There is no cure, but the condition can be treated by a combination of behavioural therapy and stimulant drugs to stay awake.
Kleine-Levin Syndrome is a rare disorder (less than 200 cases reported in the literature, according to The International Classification of Sleep Disorders, 2nd edition, 2005). Episodes of sleepiness last several days to several weeks, and occur 1-10 times per year. During sleep episodes, patients sleep as much as 18 hours a day, waking or getting up only to eat and void. During episodes, binge-eating, confusion, aggression, and hypersexuality may be present.
The NINDS website has a good summary of the disorder.
I hope this patient's doctors are writing up the case and studying her polysomnographically both during and between episodes to add to the limited scientific literature about this disorder.
Monday, February 12, 2007
New Sleep Textbook

Sleep Disorders and Neurologic Diseases, Second Edition has just been published.
Here is a description:
"Entirely devoted to the relationship between sleep and brain function, and the improved management of sleep in patients with neurologic diseases, this completely updated Second Edition includes new sections on the role of hypothalamic dysfunction in narcolepsy and the emerging relationship between sleep apnea and hypertension, heart disease, and stroke. With chapters analyzing the treatment of specific disease states, this convenient guide offers recommendations for the management of primary sleep disorders, sleep disorders secondary to well-established neurological disorders, and the neurological consequences of uncontrolled sleep conditions."
------------------------------------------
I received an advance copy a few days ago and highly recommend it to sleep physicians and trainees.
Thursday, February 01, 2007
Sleep Apnea in football players
The New York times discusses the health problems of football players, including obstructive sleep apnea:
According to a 2003 study published in The New England Journal of Medicine, 14 percent of N.F.L. players had obstructive sleep apnea, a disease that impairs breathing and is known to affect large, muscular individuals like football linemen more often than people of average size. Reggie White, a Hall of Fame defensive lineman, died at 43 in 2004 after having cardiac arrhythmia, but he also had sleep apnea, which may have contributed to his death.
With more football linemen weighing much more than 300 pounds, doctors said they expected sleep apnea to become more prevalent .
“The primary treatment for sleep apnea is to lose weight, and they can’t,” said Dr. Allan Levy, an associate team physician with the Giants, who is assisting with this week’s screening. “There’s no such thing as a 225-pound offensive lineman. We try to make certain that they understand that they’ve got to come down in weight when they retire. All of my offensive lineman from the Giants’ two Super Bowl wins have all lost at least 50 pounds. They’re all in excellent health. You see some of the other guys, and they’re just huge. They’ve got all kinds of problems.
“The problem with sleep apnea is in the neck. A 17½-inch neck is usually where the problem begins. When they sleep, the muscles relax in the body. Now the weight of their neck clasps down on their airway. They stop breathing. They momentarily wake up, then the cycle starts over again, and they never get into deep sleep. They develop heart disease and hypertension. Sleep apnea is a killer. One of the kids that played for us, we did a sleep study on, had 440 awakenings during the night.”
The most common treatment for sleep apnea involves wearing a mask that supplies a stream of air through the nose during sleep.
Increased neck size and obesity are 2 major risk factors for obstructive sleep apnea.
Friday, January 12, 2007
Some Restless Legs Medications can cause Valvular Dysfunction
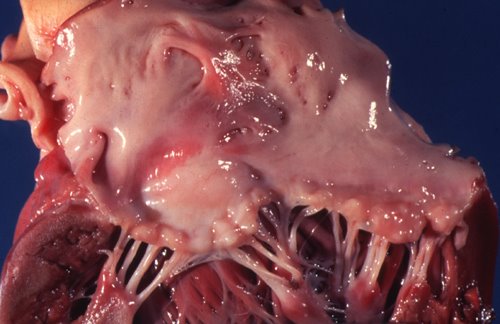
Two case-control studies published simultaneously in the January 4 issue of The New England Journal of Medicine provide some of the strongest evidence that treatment with the ergot-derived dopamine antagonists pergolide and cabergoline, commonly used in Parkinson's disease, can cause cardiac-valve dysfunction. They also suggest that the adverse effect is not caused by some other prescribed dopamine antagonists, especially those not derived from ergot.
According to a perspective by Bryan L. Roth, MD, PhD, of the University of North Carolina in Chapel Hill, that accompanies the 2 studies, the findings support prior clinical and mechanistic evidence for a link between a histologically distinct fibrotic valvulopathy and treatment with drugs that block the serotonin receptor 5-hydroxytryptamine 2B (5-HT2B). Pergolide and cabergoline have that biochemical action in common, whereas the other studied dopamine antagonists do not have significant effects on 5-HT2B, writes Dr. Roth.
Dopamine agonists are used to treat both Parkinson's disease and restless legs syndrome. The association between ergot-derived dopamine agonists and valvular dysfunction was first recognized about 5 years ago. Requip and Mirapex are the only dopamine agonists that should be used to treat restless legs syndrome.
Thursday, December 21, 2006
Nocturnal leg cramps

Cortlandt Forum has a nice short article on Nocturnal leg cramps:
By Russel Kirkby, MD, and Brian Alper, MD, MSPH
Description• Involuntary nighttime painful leg muscle contraction that does not relax
ICD-9 codes• 728.85 spasm of muscle • 729.82 cramp of limb
Prevalence• 95% of people sometime in their lives • Especially common in women and elderly
Most commonly affected muscle groups• Calf • Foot
Etiology• Most commonly no cause found• Possible causes (or associated conditions) include —Fluid and electrolyte imbalance: hypocalcemia, hyponatremia, hypomagnesemia, hypokalemia, hyperkalemia, chronic diarrhea, hemodialysis —Endocrine disease: thyroid disease, diabetes mellitus, Addison’s disease — Neuromuscular disease: nerve-root compression, motor-neuron disease, mononeuropathies, polyneuropathies, dystonias —Drugs: calcium channel blockers (nifedipine), diuretics, phenothiazines, fibrates, selective estro- gen receptor modulators (raloxifene), ethanol, morphine withdrawal —Toxins: lead, strychnine, spider bites —Congenital disease: McArdle’s disease, glycogen storage disease, autosomal dominant cramping disease —Peripheral vascular disease —Iron deficiency anemia —Liver cirrhosis, chronic alcoholism, sarcoidosis —HIV myelopathy• Pathophysiology speculative, may include reduced blood flow and oxygen supply
Likely precipitating factors• Activity excessive for condition of muscle• Sleeping prone or supine with toes fully extended • Pregnancy (insufficient calcium intake)• Older age
Complications• Insomnia • Irritability • Anxiety • Depression
Clinical evaluation• History of onset and clues to underlying condition• Drug history crucial• Local exam: arterial pulses, skin, nerves—Pulses and capillary fill (rule out vascular compromise) —Assess skin changes—Sensation/vibration
Differential diagnoses• Intermittent claudication• Peripheral neuritis• Restless legs syndrome• HIV myelopathy• Physiologic cramps due to heat, exercise, excessive activity• Electrolyte abnormalities: hyponatremia, hypokalemia, hypomagnesemia• Polycythemia• Endocrine disease: diabetes, thyroid disease, parathyroid disease, adrenal disease • Muscle diseases: glycogen storage or mitochondrial
Testing (for recurrences or underlying disease)• Electrolytes • Glucose • Blood urea nitrogen, creatinine • Calcium, magnesium, phosphate • Hemoglobin, ferritin • Zinc • Liver function tests • Thyroid function tests• HIV if appropriate• Doppler studies of arteries• Electromyelography
Nonpharmacologic management• Reassurance to exclude causes that might cause patients concern, e.g., vascular disease• Major thrust is to avoid sleep disturbance• Trial of omitting possible causative medication• Other treatments to consider—Local heat —Massage —Osteopathic manipulative therapy (OMT): myofascial release, facilitated positional release
Medications to consider• Quinine sulfate 200-400 mg nightly —Beware long-term use.—Rare but serious side effects described (disseminated intravascular coagulopathy, thrombocytopenia, pancytopenia, hemolytic uremic syndrome) —Consider monitoring complete blood count or platelets.• Other drugs similar to quinine —Hydroquinine 300 mg —Quinidine sulfate 400 mg• Other drugs not similar to quinine—Verapamil 120 mg nightly—Gabapentin (Neurontin) may reduce frequency and severity of muscle cramps.—Magnesium not clearly effective• Benzodiazepines (clonazepam, diazepam) or baclofen—Not traditionally associated with nocturnal cramp therapy but helpful in other spastic muscle conditions, e.g., tetanus, status epilepticus, and back muscle spasm —Address treatment goals of avoiding sleep disturbance.• Gastrocnemius trigger point injection of 1% lidocaine• Randomized n-of-1 trials alternating drug and placebo may determine efficacy of specific drugs for individual patients.
Prevention• Stretching exercises — e.g., nightly or twice daily • 20-minute walk may enhance stretching exercises.
See for www.dynamicmedical.com) references.
Quinine is the most commonly used treatment for this poorly understood condition; however with this medication cinchonism needs to be monitored for.
Tuesday, December 19, 2006
The Challenges of Treating Restless Legs Syndrome


The following case report appears in this month's Journal of General Internal Medicine (abstract below):
CASE REPORT
Medication Tolerance and Augmentation in Restless Legs Syndrome: The Need for Drug Class Rotation
Roger Kurlan, MD, Irene Hegeman Richard, MD, Cheryl Deeley, RNP
Restless legs syndrome (RLS) is a common condition characterized by an unpleasant urge to move the legs that usually occurs at night and may interfere with sleep. The medications used most commonly to treat RLS include dopaminergic drugs (levodopa, dopamine agonists), benzodiazepines, and narcotic analgesics. We report the cases of 2 patients with RLS who illustrate the problems of tolerance (declining response over time) and augmentation (a worsening of symptoms due to ongoing treatment) that can complicate the pharmacotherapy of RLS. We discuss the optimal management of RLS and propose strategies to overcome tolerance and augmentation such as a rotational approach among agents from different classes.
Tolerance and augmentation (see abstract above for definitions) were significant problems with Sinemet, which was previously commonly used to treat RLS. Tolerance and augmentation are less of a problem with the Requip and Mirapex, two dopamine agonists FDA approved for the treatment of RLS. However augmentation and tolerance still occur with these meds, and there is little research about the best way to deal with this vexing problem. I usually treat RLS initially with Requip or Mirapex monotherapy. If tolerance or augmentation occur, I first add another RLS agent (Neurontin, benzodiazepines, or opioids) and then later switch from 1 opioid agonist to another.
Wednesday, December 06, 2006
Mississippi Sleep Criminal
The case of John L. White, a Mississippi commercial truck driver, sounds like an accident—and now a pending law suit—that didn’t have to happen.
White of Gulfport, recently collided his vehicle into a tractor-trailer, causing the death of one man and a multiple-vehicle pile up. Sadly, White is charged with involuntary manslaughter and accused of violating sleep requirements.
The National Highway Traffic Safety Administration estimates that 100,000 police-reported crashes are the direct result of driver fatigue each year. This results in an estimated 1,550 deaths, 71,000 injuries and $12.5 billion in monetary losses. What’s more, approximately 5,600 people are killed annually in crashes involving commercial trucks. While not all of these can be attributed to sleep disorders or drowsiness, research shows that commercial drivers are at risk for everything from highway hypnosis to obstructive sleep apnea (OSA).In the case of 42-year-old trucker John White, court records say he violated commercial truck driving laws requiring at least eight hours of sleep within a certain period of time on the road. According to the Kansas City Star, White was hauling a load of bananas to a Wal-Mart distribution center when he attempted to cross over US 71 and collided with a tractor-trailer. Tragically, the driver of that vehicle, Steven B. Cousineau of Wisconsin, was pronounced dead at the scene. In addition, the crash caused two other motor vehicle wrecks, but none of the other drivers reported any injuries. The news report makes no mention of White suffering from a sleep disorder and does not clearly state that he fell asleep at the wheel. The case is focused strictly on his state of sleep deprivation while on duty. A recent study by University of Pennsylvania researchers looked at why so many commercial drivers get drowsy or fall asleep at the wheel. They concluded that the two biggest culprits are chronically insufficient sleep and obstructive sleep apnea. Of the 247 commercial drivers tested by the researchers, the percentage of drivers with two or three performance impairments after less than 5 hours of sleep was 49.5%. Clearly, there is good reason for commercial drivers to abide by sleep laws intended for their own safety and the safety of others.
Friday, December 01, 2006
Childhood sleep question
A reader e-mailed the following exam question regarding sleep disorders in children:
The Q with its alternatives is>as follows;All the following do not constitute>pathologic criteria for sleep except 1.hypnic jerk>2.increased somnolence 3.sleep myoclonus.are there any>different pathologic criteria for children other than>ICSD2.if so what are these criteria.Your reply would>be of immense help for my exams.
My answer was:
hypnic jerk is benign. Somnolence and myoclonus are pathologic.
If anyone has a better answer for this question, please post it in the comments.
Wednesday, November 15, 2006
New medication for restless legs syndrome
Requip now has a competitor. The National Sleep Foundation reports that Mirapex has been approved for the treatment of RLS:
The Food and Drug Administration (FDA) has approved Mirapex for the treatment of moderate-to-severe primary restless legs syndrome (RLS), a common condition in which an irresistible urge to move the legs impacts a person’s quality of life and ability to sleep. A recent analysis of NSF’s 2005 Sleep in America poll published in the journal CHEST found that 9.7% of adults reported symptoms of RLS at least a few times a week.
Mirapex is made by Boehringer-Ingelheim and since 1997 has been indicated for treatment of symptoms of Parkinson’s disease. In clinical trials it was shown that lower doses (than used for Parkinson’s disease) improve RLS symptoms, sleep satisfaction, and quality of life. Side effects of the drug may include hallucinations, dizziness, sweating, and nausea and Boehringer-Ingelheim warns that Mirapex may cause patients to fall asleep without any warning, even while doing normal daily activities such as driving.
Monday, November 13, 2006
New ICD-9 code for restless legs syndrome

The American Academy of Sleep Medicine reports that the ICD-9 code for restless legs syndrome is being changed from 333.99 to 333.94:
The ICD-9 Coordination and Maintenance Committee recently published an addendum announcing a change in the code for restless legs syndrome. Effective October 1, 2006, the new code is 333.94. Please note it may take time for insurance companies to institute the change. For more information, visit http://www.cdc.gov/nchs/about/otheract/icd9/maint/maint.htm
Sunday, November 05, 2006
Alcohol and sleep

Question: Will drinking a glass of wine at bedtime help me to get a better night’s sleep?
Answer:
1 to 2 drinks of an alcoholic beverage will often help a person to fall asleep. Larger amounts of alcohol, when used on a regular basis, can interfere with the ability to fall asleep. Any amount of alcohol near bedtime can lead to awakenings later in the night, as the effect of alcohol is wearing off.
Alcoholism can lead to insomnia that may last for 2 years after alcohol use is discontinued.
Alcohol can make snoring and obstructive sleep apnea worse. Persons with untreated sleep apnea should avoid alcohol near bedtime.
Rather than treating your insomnia with alcohol, a better option is consulting with a primary care physician or sleep specialist for safer and more effective treatments.
Saturday, October 07, 2006
Bipolar Disorder and Sleep

Sleep disturbance is a well-recognized feature of acute psychiatric illness, and is included in the diagnostic criteria of many of the affective and anxiety disorders. Recent research has found that disrupted sleep and sleep complaints are common in patients with affective disorder even between mood episodes. Treatment of disrupted sleep and the maintenance of a regular sleep/wake cycle are important components of the prophylaxis of mood episodes in bipolar disorder.
Sleep disturbance is a cardinal feature of bipolar disorder. During acute mania, patients exhibit markedly reduced sleep time and report a reduced need for sleep. Even when euthymic, sleep disturbance is common. In a recent study, 55% of euthymic bipolar patients had chronic insomnia (Harvey et al 2005). Children with bipolar disorder (who often display ultradian rapid cycling rather than distinct mood episodes) exhibit reduced sleep efficiency and frequent nocturnal awakenings (Mehl et al 2006).
Clinical vignette
JW, a single 25 year-old female with bipolar type I disorder, had been relatively stable for the last three years on a regime of lithium 600 mg twice daily and Ambien (zolpidem) 10 mg at bedtime. She had not had a distinct mood episode since her last episode of bipolar mania three years ago. She obtained 7 to 8 hours of sleep at night, and was satisfied with her job as a respiratory therapist working for a durable medical equipment (DME) company.
Four weeks ago, the DME company went out of business, and JW took a job as a sleep technician working for a growing sleep disorders center. This exciting job involved working 8 pm to 6 am Tuesday through Friday. JW was only able to sleep 5-6 hours after her shift, even with the aid of Ambien. She slept about seven hours on nights she was not working.
Three days ago, on a Saturday morning, JW felt unusually energized as she was finishing her shift. She drove home and spent the next sixteen hours cleaning her house from top to bottom. JW then slept for an hour and went to a dance club. She left the dance club when it closed at 3 am and returned to her house, where she slept for two hours. She exercised extensively on Sunday and showed up at the sleep center Sunday night. She told her co-workers she was there because she was now the owner of the sleep center and she wanted to make sure they were doing their jobs right. She was talking rapidly and pacing. JW became agitated when the the other sleep technicians refused to take orders from her. The medical director was called. He, with great difficulty, was able to convince her to go to the ER. The medical director and a technician drove her to the ER, where treatment was begun for a bipolar manic episode.
Comment: JW developed a manic episode with symptoms of grandiosity, decreased need for sleep, rapid speech, and increased goal-directed activity. A change in sleep habits can precipitate a bipolar mood episode. Night work and shift work have a destabilizing influence on bipolar disorder.
Bipolar disorder is treated with mood stabilizing agents such as sodium valproate, carbamazepine, or lithium. Addition of an antidepressant may be necessary to control bipolar depression. The maintenance a stable sleep/wake cycle, as well as regularization of the circadian rhythm, are key components of a relatively new psychotherapy for bipolar disorder, Interpersonal and Social Rhythm Therapy (IP-SRT). IP-SRT is most effective for mood episode prophylaxis in the maintenance phase of bipolar, and in individuals without significant medical comorbidity or anxiety (Frank et al 2005).
---------------------------------------------------------------------
The above is from a chapter I am writing for Medlink Neurol0gy entitled "Sleep disorders associated with mental disorders". It is copyrighted by Medlink Neurology.
Tuesday, October 03, 2006
Viagra worsens sleep apnea
The National Sleep Foundation reports:
Each year, millions of men in American seek treatment for erectile dysfunction (ED), a condition that is often associated with obstructive sleep apnea (OSA). Since its introduction in 1998, Viagra has become the most common form of treatment for ED. It works by enhancing the effects of nitric oxide, a compound that relaxes muscles in the penis and allows for increased blood flow, triggering an erection. Now a new study by a team of Brazilian and American researchers suggests that a single 50-mg dose of Viagra may actually worsen symptoms of obstructive sleep apnea (OSA). The study involved 14 middle-aged men with severe OSA in a double-blind crossover study. Using polysomnography, the researchers analyzed the severity of symptoms and found a significant increase following a dose of Viagra compared to placebo.
Here is the abstract for the study:
A Double-blind, Placebo-Controlled, Crossover Study of Sildenafil in Obstructive Sleep Apnea
Suely Roizenblatt, MD, PhD; Christian Guilleminault, MD, BiolD; Dalva Poyares, MD, PhD; Fátima Cintra, MD, PhD; Adriana Kauati, PhD; Sergio Tufik, MD, PhD
Arch Intern Med. 2006;166:1763-1767.
Background Sildenafil prolongs the action of cyclic guanosine monophosphate and nitric oxide by inhibiting cyclic guanosine monophosphate–specific phosphodiesterase 5. It is largely used for erectile dysfunction, a highly prevalent condition in obstructive sleep apnea. Because nitric oxide promotes upper airway congestion, muscle relaxation, and pulmonary vasodilation, the aim of this study was to establish the impact of a single 50-mg dose of sildenafil on the sleep of patients with severe obstructive sleep apnea.
Methods Fourteen middle-aged men with severe obstructive sleep apnea were consecutively selected for this double-blind, placebo-controlled, crossover study. Exclusion criteria were obesity, cardiovascular and/or respiratory disease, and conditions that interfere with sleep. All-night polysomnography was preceded by a single 50-mg dose of sildenafil or matching placebo randomly administered at bedtime, after a washout period of 1 week.
Results In comparison to placebo, a single 50-mg dose of sildenafil significantly increased the percentage of total sleep time with an arterial oxygen saturation of less than 90% (mean ± SD, 14.2% ± 9.1% vs 8.5% ± 3.2%, P<.01), without a difference in the nadir of oxygen desaturation. The mean arterial oxygen saturation also decreased (92.1% ± 1.91% vs 93.8% ± 1.3%, P = .02), and the desaturation index increased (30.3 ± 18.1 events per hour vs 18.5 ± 14.6 events per hour, P<.001). There was an increase in apnea-hypopnea index (42.4 ± 25.5 events per hour vs 34.6 ± 24.1 events per hour, P = .01), involving mostly obstructive events.
Conclusion In patients with severe obstructive sleep apnea, a single 50-mg dose of sildenafil at bedtime worsens respiratory and desaturation events.
Based on this study, physicians should be cautious in prescribing Viagra, Cialis, or Levitra in patients with known or suspected untreated severe obstructive sleep apnea.
Saturday, August 26, 2006
Mothers and Sleep
Most mothers would agree that their sleep habits are a lot different than they were before having children. Lazy weekend mornings are a thing of the past and most find fewer hours to catch some shut-eye during the week, too. Sonia Cannon, of Jackson, can relate. Erin, her 7-year-old daughter, takes up most of her time in the evenings. “During the school year, after helping Erin with homework, preparing dinner and putting her to bed, I feel like my night has just begun for relaxation,” says Cannon. “Sleep is the last thing on my mind.” Moms are not alone. According to recent studies, Americans in general are getting less sleep than ever before. Up to one-third of Americans have symptoms of insomnia; sleep apnea and restless leg syndrome are also common. Most untreated sleep disorders are associated with high blood pressure, heart attack, stroke and psychiatric problems. “Most people need seven to eight hours of sleep per night,” says Dr. Michael Rack, medical director for Somnus Sleep Clinic in Flowood. “That doesn’t change. Once we reach adulthood, our sleep needs remain the same.” Rack says that one hot topic in the news lately is the relationship between sleep and obesity. “Sleep deprivation defined as less than six hours of sleep per night, has been linked to weight gain,” adds Rack. Many moms have accepted lack of sleep as a fact of life. So how do you know if you have a real problem? Dr. Alp Baran, director of the Sleep Disorders Center at the University of Mississippi Medical Center, says that sleep disorders are more common than we think. “I tell people all the time that snoring is not normal,” he says. “If you snore, see your doctor for treatment.” Sleeping longer on weekends can be another sign of a possible problem. A mother of two teenagers and two college kids, Teresa Adams, of Madison, runs a busy household, volunteers at church and juggles graduate school every day. “I don’t get much sleep and my body is used to it now. I know it’s not a healthy lifestyle,” she says. Cannon says, “I have to make sure all of my daughter’s needs are met on a daily basis even if I’m tired from a long day at work.” Both women admit that a cup of coffee is often the only way they can jump-start the day. It can be quite a challenge to find time for those much-lauded eight hours between careers, carpool and mealtimes. Rack says set a sleep schedule and stick to it. “Going to bed and waking up at the same time every day, including weekends, is important.” Both Baran and Rack agree that avoiding caffeine and alcohol late in the day, forgoing a heavy meal or strenuous exercise before bedtime, and banishing the television from the bedroom can also help women get to sleep faster and more restfully. Rack does note, however, that exercise earlier in the day can actually contribute to a good night’s rest. Additionally, Baran reminds moms that getting kids into a good bedtime routine will help moms rest easier. Rack and Baran also suggest that married couples ask their partners what they are doing during the night — snoring, tooth grinding, etc. “Share this information with your doctor to help him/her get to the root of the problem,” Rack adds. Most sleep disorders can be easily treated with medication, counseling, behavioral therapy or a combination of treatments. So rest easy!
http://www.print2webcorp.com/news/Jackson/MissParentingResource/20060801/p19.asp
http://www.print2webcorp.com/news/Jackson/MissParentingResource/20060801/p19.asp
Friday, August 18, 2006
Thumb Ring for Sleep Apnea


I just learned that a reflexologist in Jackson MS is using "thumb rings" to treat sleep apnea. I found this add for "The Anti Snor Therapeutic ring" on the web:
From Florence Cardinal,Based on acupressure
Guide Rating -
The Anti Snor Therapeutic ring uses the concepts of acupressure to improve sleep. It's designed to reduce snoring, sinus problems and restless sleep.
Acupuncture/acupressureAcupuncture has been around for hundreds of years. Acupuncture without needles is called acupressure. Both work on the many meridians that run throughout the body carrying energy. The use of acupuncture or acupressure is said to clear stoppages of this energy.
The Anti Snor Therapeutic ring uses the concepts of acupressure to improve sleep. It's designed to reduce snoring, sinus problems and restless sleep. This is accomplished by wearing a ring that's crafted with tiny silver balls that apply light pressure to the base of the little finger of the left hand.
How the ring worksThis pressure stimulates acupressure points which, in turn, stimulate the meridian that leads to the small intestine, through the body to the heart. This meridian continues up the arm the face, jaw and head.
Stimulating this meridian frees the energy in the small intestine and heart meridians, and has a calming effect on the entire body. The It's excellent those suffering from stress induced insomnia
I don't think that it works.
Monday, August 14, 2006
CPAP use by Children

SAN JUAN, P.R. — Continuous positive airway pressure can be effective for obstructive sleep apnea in children, but parents must be persistent to ensure children's acceptance of the treatment, Dr. Ann C. Halbower said at a meeting sponsored by the American College of Chest Physicians.
Obstructive sleep apnea (OSA) is present in 2%–3% of children, and peaks at 3–6 years of age—which is also the peak age for adenotonsillar hypertrophy. The presentation depends on the age of the child: In the infant, it might present as sudden infant death syndrome (SIDS). Toddlers with OSA will have hyperactivity, school-age children will have failure to thrive and poor school performance, and adolescents may present with obesity and excessive daytime sleepiness.
Adenotonsillectomy is the first-line therapy for children with OSA. When that is not successful, continuous positive airway pressure (CPAP) can promote more ordered breathing during sleep and relieve OSA.
CPAP can be problematic in children, however. “It's very hard to take. Little kids don't like it, but there are things parents and physicians can do to help make CPAP more palatable,” said Dr. Halbower, who serves as medical director of the pediatric sleep disorders program at Johns Hopkins University, Baltimore. Dr. Halbower recommended introducing the device slowly to minimize the fear factor. Put on the mask while the child is awake and doing an activity that is fun and pleasurable, she said.
The worst thing you can do is put the mask on while the child is asleep. “If they wake up and find themselves wearing the mask, they'll panic,” Dr. Halbower said
Another trick that can be used to make CPAP part of the child's normal bedtime routine, along with brushing the teeth and a bedtime story. Other children who use CPAP are wonderful ambassadors for the device and can help relieve anxiety with a show-and-tell. Videos are good for this as well.
Despite these efforts, some children will do everything to resist attempts to put on the mask. Many parents will remove the mask in response to their child's distress.
That is a big mistake, Dr. Halbower said, because it just strengthens the child's escape and avoidance behavior. Eventually, the parent gives up.
Behavioral training can help parents block or prevent their child's avoidance behavior by using brief verbal prompting, redirection to a specific task, and if necessary, physically blocking escape while gently guiding the child to remain in the situation.
The child's attempt to remove the mask must be physically interrupted and the mask replaced immediately every time the child removes it. She said these behavioral techniques are used in her clinic under the guidance of Keith Slifer, Ph.D., a behavioral psychologist. [The techniques] “have proved very successful,” Dr. Halbower said.
Parents should also plan for safety in children who cannot remove the mask during emergencies, Dr. Halbower cautioned.
Use a nasal mask instead of a full-face mask, or have an emergency pull string that can disengage the mask to prevent aspiration or asphyxiation if the child vomits.
It is important for parents to establish a consistent bedtime routine that lasts about 30 minutes, Dr. Halbower explained. Such a routine includes soothing activities, and it always ends with the child putting on the CPAP mask, lying down, and going to sleep.
“Persistence and patience are key,” she said.
Adenotonsellectomy usually cures childhood obstructive sleep apnea. However, many obese children with OSA will end up needing CPAP.
Thursday, August 10, 2006
Traveling with CPAP

... tips to help CPAP users increase compliance while traveling:
Inform the airline about using CPAP therapy while onboard. Many airlines have strict policies regarding using CPAP therapy while in flight, but by calling beforehand, CPAP users can minimize the hassle that is sometimes involved with using a CPAP device while flying.
Use a battery-powered CPAP device or Bring an extension cord. Travel with extra filters.
Pack distilled water for humidifiers. Keeping a small bottle of distilled water in a container is an easy way for CPAP users to carry along the water needed for humidifiers, Larkin said.
From Sleep Review Magazine . I tried to find a picture of someone wearing CPAP on an airplane to illustrate this post, but apparently there is no picture like this on the internet.
Thursday, August 03, 2006
Valerian for Insomnia

Valerian is a medicinal herb that may be useful in the treatment of insomnia. It is thought to increase the level of GABA in the synaptic cleft.
The National Sleep Foundation reports:
Herbal remedies are used around the world for a variety of ailments, including sleep disorders. For many years, sleep researchers have studied herbal compounds such as valerian in hopes of finding new treatments for insomnia and other sleep problems. Sold in the United States as a dietary supplement and loosely regulated by the FDA as a food substance, valerian is available in the form of a tea, tincture, capsule, or tablet. People try valerian as a natural sedative for nervousness and insomnia. With so many Americans suffering from insomnia - 54% report symptoms at least a few nights a week or more, according to the National Sleep Foundation’s 2005 Sleep in America poll – it’s no wonder that insomnia sufferers would seek out remedies.
But does valerian really work? The latest word comes from the Office of Dietary Supplements (ODS) at the National Institutes of Health (NIH) in their recently updated and thorough fact sheet on valerian for the treatment of insomnia. It states that while evidence from some clinical studies suggests that valerian may be useful for insomnia, others do not. Also, in its State-of-the-Science Conference Statement on Manifestations and Management of Chronic Insomnia in Adults, NIH found that only non-benzodiazepine medications and cognitive behavioral therapy (CBT) have evidence for safety and efficacy to support their use for the treatment of insomnia. This report also found that insomnia often occurs in association with other disorders, in which case, seeking medical treatment would be recommended over the use of self-treatments such as valerian.
NIH also warns, "Like drugs, herbal or botanical preparations have chemical and biological activity. They may have side effects. They may interact with certain medications. These interactions can cause problems and can even be dangerous. Before taking an herb or a botanical, consult a doctor or other health care provider-especially if you have a disease or medical condition, take any medications, are pregnant or nursing, or are planning to have an operation. Before treating a child with an herb or a botanical, consult with a doctor or other health care provider."
Here is the NIH fact sheet on valerian.
Monday, July 24, 2006
Sleep is Underrated

Katie Couric, the former "Today" co-host and future "CBS Evening News" anchor stated in an interview: “I took the entire month of June off,” said Ms. Couric. “I found that sleep is very underrated and it was a great time for me to relax and spend quality time with my children.”
Thursday, June 29, 2006
Rich people get more sleep

In a study of sleep characteristics in 669 adults in Chicago who were compared by sex and race, investigators found that blacks got less sleep than whites, while men got less sleep than women.
Furthermore, the wealthier you are, the more sleep you're likely to get, Dr. Diane S. Lauderdale of the University of Chicago and her colleagues found.
"There was an expectation that people with very demanding jobs in terms of high status, high income, would be getting less sleep, and that was not true," Lauderdale told Reuters Health in an interview. The findings could help explain why blacks suffer from more health problems than whites, she added.
Monday, June 12, 2006
Short Naps are Better
Thinking about taking a nap, but not sure how much napping will help you wake up refreshed? A new study finds that ten minutes may be the magic number when it comes to napping. The study of 24 healthy, young adults who were good sleepers and not regular nappers investigated what would be most effective after a night of five hours of sleep – no nap, a five minute, ten minute, twenty minute or thirty minute nap. Participants took afternoon naps at 3 p.m., and their performance post-nap was measured for three hours. Benefits of the five-minute nap were similar to taking no nap, while twenty and thirty-minute naps offered improvements up to an hour and a half after the nap, though immediately following these naps there was a period of reduced performance, sleep inertia and sleepiness. In the end, the ten-minute nap yielded the most benefits with the least side effects. This nap triggered improvements in cognitive function, sleepiness, fatigue, vigor, etc., and the effects lasted for up to 155 minutes. Researchers believe further investigation is needed to understand what processes occur in the first ten minutes of sleep and how they may provide benefit.
From the National Sleep Foundation. Here is the actual abstract:
A Brief Afternoon Nap Following Nocturnal Sleep Restriction: Which Nap Duration is Most Recuperative?
Volume :
29
Issue :
06
Pages :
831-840
View PDFEmail a Friend
Amber Brooks, PhD; Leon Lack, PhD
School of Psychology, Flinders University, Adelaide, SA, Australia
Study Objectives: The purposes of this study were to compare the benefits of different length naps relative to no nap and to analyze the electroencephalographic elements that may account for the benefits. Design: A repeated-measures design included 5 experimental conditions: a no-nap control and naps of precisely 5, 10, 20, and 30 minutes of sleep. Setting: Nocturnal sleep restricted to about 5 hours in participants’ homes was followed by afternoon naps at 3:00 PM and 3 hours of postnap testing conducted in a controlled laboratory environment. Participants: Twenty-four healthy, young adults who were good sleepers and not regular nappers. Measurements and Results: The 5-minute nap produced few benefits in comparison with the no-nap control. The 10-minute nap produced immediate improvements in all outcome measures (including sleep latency, subjective sleepiness, fatigue, vigor, and cognitive performance), with some of these benefits maintained for as long as 155 minutes. The 20- minute nap was associated with improvements emerging 35 minutes after napping and lasting up to 125 minutes after napping. The 30-minute nap produced a period of impaired alertness and performance immediately after napping, indicative of sleep inertia, followed by improvements lasting up to 155 minutes after the nap. Conclusions: These findings suggest that the 10-minute nap was overall the most effective afternoon nap duration of the nap lengths examined in this study. The implications from these results also suggest a need to consider a process occurring in the first 10 minutes of sleep that may account for the benefits associated with brief naps.
Thursday, June 08, 2006
Dear Abby says to go see a Sleep Specialist
DEAR ABBY: I am a 37-year-old married woman with a problem. My mother committed suicide when I was 18, and I have never dealt with my loss. The day after she died, my father bagged up all of her possessions and gave them to charity. I tried talking to him about her, but he told me she was "gone" and I had to move on. I guess I have just put my pain on the back burner all these years.
For the last five years or so, I have been sleepwalking and having horrible nightmares about my mother's death. My husband tells me I carry on conversations with him, but that I am not really "there." I also take baths when I'm technically asleep. On one occasion, I woke up behind the wheel of my truck in my garage. I don't know if I went out driving or not, but the thought terrifies me.
I am afraid I will hurt myself, or possibly others, in my zombie-like state. Any advice you can give me would be greatly appreciated. -- OUT OF IT IN LAS VEGAS
DEAR OUT OF IT: Please accept my deepest sympathy for the tragic loss of your mother. The first thing you must do is ensure that your husband has the keys to your truck at bedtime.
Then, contact your physician and ask for a referral to a sleep disorder specialist for an evaluation. Some people experience the symptoms you have described as a side effect from certain sleep-aid medications. However, if you are not taking anything, you may have a treatable sleep disorder.
After that, ask your doctor to refer you to a licensed psychotherapist who can help you deal with the emotions you have kept buried all these years since your mother's death. Once your feelings are out in the open, you will be able to deal with them -- and discussing them with a professional will help you more quickly through the process.
Tuesday, June 06, 2006
The difference between CPAP, BiPAP, and auto-CPAP
A reader asks "I've been on a CPAP for years, but my sleep specialist is putting me on an AutoPAP. In the meantime, my DME has me on a loaner BiPAP and I feel a lot better even after one night's sleep.Also, does the difference in machines do anything in reducing long term complications"
CPAP, continuous positive airway pressure, delivers a single continuous level of pressure. CPAP is usually effective in treating obstructive sleep apnea. BiPAP delivers a higher pressure while breathing in, and a lower pressure while breathing out. BiPAP can be used to treat obstructive sleep apnea and is sometimes effective in treating central sleep apnea. I t can also be used to assist ventilation in various pulmonary and neurological disorders. Auto-CPAP can be used in 2 different manners: 1) to vary pressure during sleep for a person who has varying pressure requirements (for example, needing a higher pressure during REM sleep) and 2) can be used on a temporary basis to do a CPAP titration. In cases in which patients have had a CPAP titration in the sleep lab but I'm still not quite sure of the exact optimal pressure, I sometimes send them home with an auto-CPAP machine for a few nights. The machine generates a computerized printout that helps me pick the right pressure.
In OSA, the differences in the machines make no difference in reducing complications as long as the patient is compliant with treatment and receiving an effective pressure(s).
Monday, June 05, 2006

Sunday, June 04, 2006
Measuring Sleepiness in Children

Clinical Psychiatry News has a good article about the use of the Multiple Sleep Latency Test in pediatric patients:
Although a simple clinical evaluation can provide a fairly good indication as to whether the child has daytime sleepiness, it's often difficult to estimate how severe the problem is. “The multiple sleep latency test (MSLT) can help answer that question in an objective way that's been standardized and well validated,” said Dr. Hoban of the sleep disorders center at the University of Michigan, Ann Arbor.
Unlike certain questionnaire-based assessments, the MSLT has been validated in children, and provides reliable results as long as the child is at least 6 or 7 years old. However, the test is expensive and time consuming to perform and must be conducted in a sleep lab. The MSLT may be useful when a child has excessive daytime sleepiness but the clinical history, examination, and polysomnography reveal no specific cause. Dr. Hoban recommended judicious use of the MSLT in evaluations of sleep-disordered breathing, circadian rhythm disorders, narcolepsy, and other disorders of excessive sleepiness.
Developed initially at Stanford (Calif.) University in the 1970s, the MSLT has a simple premise: People who are sleepy will fall asleep faster than those who are not.
After a night of polysomnography to screen for some sleep disrupters and to ensure that the patient has had a good night's sleep, the child is given four or five chances to nap in a dark, quiet environment, with each nap separated by about 2 hours. If the child fails to fall asleep (as measured by EEG tracings) within 20 minutes, the nap opportunity ends. Otherwise the child is allowed to sleep for 15 minutes following the first epoch of sleep.
In addition to the latency of sleep, the MSLT records the presence of sleep-onset REM periods (SOREMPs). The presence of SOREMPs correlates strongly with the presence of narcolepsy. Narcoleptic patients also typically have a sleep latency of 5 minutes or less.
The article goes on to give normative data for interpreting the MSLT in pediatric patients:
Normal adults have a sleep latency of about 15 minutes, but normal latencies in children can be much longer. Detailed studies have correlated mean sleep latencies with Tanner stage. Children in Tanner stage 1 take an average of 19 minutes to fall asleep, whereas those in stage 5 take about 16.6 minutes; older adolescents take a mean 15.7 minutes to fall asleep.
“The net result of this is that in preadolescent children you can have a sleep latency of 14 or 15 minutes that would be considered solidly normal by adult standards but substantially abnormal for a child,” Dr. Hoban said.
For moreinformation about the use of the MSLT in the diagnosis of narcolepsy, see here.
Tuesday, May 09, 2006
Nocturia and Obstructive Sleep Apnea
From the National Sleep Foundation:
Who would have thought that sleep apnea might be responsible for frequent trips to the toilet at night, but a recent study of 97 individuals (75 men and 22 women), found that individuals with sleep apnea who also experienced nocturia (frequent urination at night) benefited from continuous positive airway pressure (CPAP) treatment. Researchers at the Institute of Urology in Tel Aviv, Israel found that individuals awoke to urinate 2.5 times on average per night before treatment, and after being treated with CPAP, the majority of participants only awoke 0.7 times per night on average. Of the 97 participants, 73 reported improvement in nocturia. The results indicate that CPAP treatment for obstructive sleep apnea (OSA) may also have positive effects on nighttime urination.
Nocturia is a common symptom of sleep apnea. This has been well know to sleep specialists. This study demonstrates that CPAP is an effective treatment for this OSA symptom. One of these days I'll get around to posting an explanation of how osa causes nocturia.
Friday, April 21, 2006
Vice President Cheney

Vice President Dick Cheney appears to nod off during a news briefing by President Bush and Chinese President Hu Jintao in Hu's first Oval Office visit. (Tim Sloan/AFP/Getty Images)
I don't think he's sleeping, the Vice President was just pondering matters of national security with his eyes closed.
Sunday, April 16, 2006
Insomnia can lead to desperation
Drudge links to this story about a man who backed out of re-enacting the Crucifixion.
The man was considering re-enacting the Crucifixion as part of a spiritual journey to regain his faith.
What led to his loss of faith?
“His insomnia was a major problem. He used to lie in bed all night praying for God to let him sleep and He never answered so he began to think there was no God.”
The man was considering re-enacting the Crucifixion as part of a spiritual journey to regain his faith.
What led to his loss of faith?
“His insomnia was a major problem. He used to lie in bed all night praying for God to let him sleep and He never answered so he began to think there was no God.”
Monday, March 27, 2006
Sleep Chat
A reader posted this comment about a live web chat about sleep: Thought you all might like to know the WebMD sleep expert, Dr. Michael Breus, is going be hosting a live web chat on Saturday night (April 1) for two hours beginning at 11:30pm EST. He's going to answer sleep-related questions in a chat room on www.sleepbetter.org. Apparently, this all part of Carpenter CO. National Sleep Better Night.
Wednesday, March 22, 2006
Update on the Relationship between Sleep and Metabolism
The Relationship between Sleep and Metabolism
Karine Spiegel, PhD, and colleagues published an article in the December 7, 2004 issue of the Annuals of Internal Medicine that suggests that sleep restriction can lead to weight gain. They found that sleep restriction (4 hrs /night) leads to decreased levels of the hormone Leptin and increased levels of Ghrelin, another hormone. The alteration of the levels of these appetite and energy regulating hormones was associated with increased hunger and appetite in the study. This study adds to the evidence linking insufficient sleep to obesity.
More recently, Dr. Henry Klar Yaggi and colleagues reported on a 15-year study that examined the association between sleep duration and the risk of developing type 2 diabetes mellitus. The prospective observational Massachusetts Male Aging Study found that men reporting short sleep duration (6 or less hours per night) and men reporting long sleep duration (more than 8 hours per night) were at significantly increased risk for developing diabetes compared to those getting 7-8 hours of sleep.
Insufficient nocturnal sleep can be caused by either a sleep disorder or voluntary sleep deprivation. Excessive sleep is usually caused by an underlying sleep disorder. Abnormal nocturnal sleep durations have been linked with obesity, impaired glucose tolerance, and diabetes mellitus.
It is important for physicians to counsel their overweight and obese patients to allow for 8 hours of sleep per night. Since obstructive sleep apnea is both a cause and consequence of obesity, practitioners should screen their obese patients for this common disorder. Useful symptoms to ask about include snoring, prolonged sleep duration, frequent nocturnal awakenings, and excessive daytime sleepiness.
Ambien and Sleepwalking
The American College of Physicians reports:
Widely prescribed sleep aid prompts complaints of sleepwalking
A widely used sleep aid has sparked concerns about sleepwalking and other unusual behaviors among people prescribed the drug.
Cases of sleepwalking related to use of zolpidem tartrate (Sanofi-Aventis’s Ambien) have been reported in medical journals and by sleep experts, said the March 14 Washington Post. Some patients also have reported evidence of nocturnal eating after taking the drug, the article said, and of having no memory of those incidents when they awake.
The drug, which accounted for more than 24 million prescriptions in 2004, has prompted more sleepwalking reports to the FDA than all other sleep medications combined, said the Washington Post. In addition, five cases were reported in a 2002 edition of the journal Sleep Medicine while researchers at the Minnesota Regional Sleep Disorders Center reported 19 cases at a medical conference last year.
The drug’s label acknowledges somnambulism as a rare but potential side effect, along with other potential central nervous system effects, that have been reported in fewer than one in 1,000 patients, said the article. Zolpidem tartrate is among a group of newer sleep aids that are considered safer and less addictive than older drugs, the Washington Post reported, adding that the FDA did not raise questions about the side effects before approving the drug in 1993.
The FDA adverse event report databases show that 207 somnambulism reports were made between 1997 and June 2005, said the Washington Post. Most physicians reporting the episodes listed the cause as unknown but 48 linked them to zolpidem tartrate. By comparison, there were 18 reports filed about benzodiazepines, an older class of sleep aids that includes six drugs.
The Washington Post is online.
Monday, March 20, 2006
More Psychiatrists are going into Sleep Medicine
Psychiatric News reports that psychiatrists are becoming increasingly attracted to a career in sleep medicine:
A woman hospitalized for treatment of her mood disorder snored so loudly that other patients complained. A sleep study showed she had severe obstructive sleep apnea.
After using a continuous positive airway pressure (CPAP) device that delivers air via a mask worn in sleep, she felt more focused and alert. "Her mood improved, and we were able to make greater inroads into her psychiatric problems," related William Clemons, M.D., then a resident in psychiatry at West Virginia University in Morgantown.
The contribution of a previously unrecognized sleep disorder to the woman's psychiatric illness proved a signal event for Clemons. He pursued a sleep-medicine fellowship at the University of Michigan, completing the one-year program in 2004. He now practices sleep medicine at the Baptist Sleep Institute in Knoxville, Tenn.
"We are seeing an explosion of interest in sleep medicine as a career option for psychiatrists," said Michael Sateia, M.D., a professor of psychiatry and chief of sleep medicine at Dartmouth Medical School. This interest is reflected in the American Board of Medical Specialties' (ABMS) approval last year of sleep medicine as a subspecialty for physicians practicing psychiatry, neurology, internal medicine, and pediatrics, he noted. ABMS recently added otolaryngology to the list.
Starting in 2007, the American Board of Internal Medicine will administer the sleep-medicine board exam, with certification conferred by boards overseeing the specialties listed above. The exam formerly was given by the American Board of Sleep Medicine.
"The new exam acknowledges that sleep medicine involves a sufficient body of knowledge and skill sets to qualify as an independent medical subspecialty," said Lawrence Epstein, M.D., president of the American Academy of Sleep Medicine (AASM) and regional medical director for Sleep HealthCenters in Boston.
The Accreditation Council for Graduate Medical Education (ACGME) has approved 24 sleep-medicine fellowships nationwide. ACGME recognition means that funding for fellowships is available from the Centers for Medicare and Medicaid Services. Fellowships typically provide an annual stipend of about $60,000.
Allen Richert, M.D., the psychiatry residency training director at the University of Mississippi Medical Center, thinks sleep medicine education belongs in the psychiatry residency.
"Sleep disorders and sleep deprivation contribute to depressed mood, irritability, attention deficits, and sleepiness," he said. "Psychiatrists need experience with hypnotic medications and cognitive behavioral therapy for insomnia."
Patients with sleep disorders benefit from a psychiatric perspective, he added. "Psychiatrists understand how patients' emotions drive behavior."
Psychiatrists interested in sleep medicine should contact their local sleep disorders centers, suggested Daniel Buysse, M.D., a professor of psychiatry at the University of Pittsburgh School of Medicine. "Many centers are looking for more input from psychiatrists to help them manage patients with sleep disorders and psychiatric comorbidity."
Friday, March 03, 2006
Practice Parameters for BiPAP and CPAP
The American Academy of Sleep Medicine has issued "Practice Parameters for the Use of Continuous and Bilevel Positive Airway Pressure Devices to Treat Adult Patients With Sleep-Related Breathing Disorders"; here is the abstract:
Positive airway pressure (PAP) devices are used to treat patients with sleep related breathing disorders (SRBD) including obstructive sleep apnea (OSA). Currently, PAP devices come in three forms: (1) continuous positive airway pressure (CPAP), (2) bilevel positive airway pressure (BPAP), and (3) automatic self-adjusting positive airway pressure (APAP). After a patient is diagnosed with OSA, the current standard of practice involves performing full, attended polysomnography during which positive pressure is adjusted to determine optimal pressure for maintaining airway patency. This titration is used to find a fixed single pressure for subsequent nightly usage. A task force of the Standards of Practice Committee of the American Academy of Sleep Medicine reviewed the available literature. Based on this review, the Standards of Practice Committee developed these practice parameters as a guideline for using CPAP and BPAP appropriately (an earlier review and practice parameters for APAP was published in 2002). Major conclusions and current recommendations are as follows: 1) A diagnosis of OSA must be established by an acceptable method. 2) CPAP is effective for treating OSA. 3) Full-night, attended studies performed in the laboratory are the preferred approach for titration to determine optimal pressure; however, split-night, diagnostic-titration studies are usually adequate. 4) CPAP usage should be monitored objectively to help assure utilization. 5) Initial CPAP follow-up is recommended during the first few weeks to establish utilization pattern and provide remediation if needed. 6) Longer-term follow-up is recommended yearly or as needed to address mask, machine, or usage problems. 7) Heated humidification and a systematic educational program are recommended to improve CPAP utilization.8) Some functional outcomes such as subjective sleepiness improve with positive pressure treatment in patients with OSA. 9) CPAP and BPAP therapy are safe; side effects and adverse events are mainly minor and reversible. 10) BPAP may be useful in treating some forms of restrictive lung disease or hypoventilation syndromes associated with hypercapnia.
Recommendation number 7 is significant. This should help patients get insurance reimbursement for having heated humidifiers added to their CPAP machines.
Thursday, March 02, 2006
Sleep Searches
One of my brothers-in-law (David) sent me the following link to the Yahoo Buzz Index:
http://buzz.yahoo.com/buzz_log/entry/2006/02/28/0300/
Concerned by the results of a new poll showing Americans aren't getting the shuteye they should, we decided to get under the covers of sleep searches. We snuggled up close to our top 10 sleep queries...
Sleep Apnea
Sleep Number Bed
Sleep Disorders
Sleep Deprivation
Sleeping Pills
Sleepwear
Sleep Paralysis
Sleeper Sofas
Sleep Aids
Sleepwalking Is eight hours of comfortable rest just a dream, or are you spending your sleepy time in a deep REM state? The thought of a nice long snooze got us daydreaming about the top 10 dream searches. Picture, if you will...
Dream Dictionary
Dream Interpretation
Meaning of Dreams
Dream Analysis
Dream Moods
Dream Symbols
Lucid Dreaming
Dream Journal
What Do Dreams Mean
Dream Poems
Subscribe to:
Posts (Atom)
